

Freedom that holds.
Heroin recovery fails most often not in detox but in the months after, when the body is clear, tolerance is gone, and the life is still the one that used. The Rebuild Method exists for exactly that gap.
The relief that became the cage.
Heroin offers what trauma, pain, and despair were begging for, total relief, and then charges everything for it. Tolerance escalates, the dose chases the first time, and today’s supply is routinely mixed with fentanyl, so no one using it can know what a given dose contains.
Withdrawal, while rarely dangerous the way alcohol’s is, is hard enough that fear of it keeps people using for years. Managed medically, it is a matter of days, held, slept, fed, and supervised, not the cliff people imagine.
- Use that moved from occasional to organizing
- Withdrawal sickness driving the schedule
- Escalating routes of use
- Isolation from everyone who knew you before
- An overdose, yours or someone close to you
Heroin, through the four domains.
Through the wall
Medically supervised withdrawal, comfort medications, buprenorphine or naltrexone where it fits, psychiatric oversight, and 1:1 presence through the worst nights.
What it was relieving
Trauma and despair don’t leave with the substance. They are treated at the same time, through trauma-focused therapy and psychiatric care.
A life worth protecting
New structure, severed supply lines, repaired relationships, and identity work, because freedom needs something to be for.
Five things to know first.
- Heroin sold today is commonly mixed with fentanyl, which the CDC describes as up to 50 times stronger than heroin and impossible to see, taste, or smell.
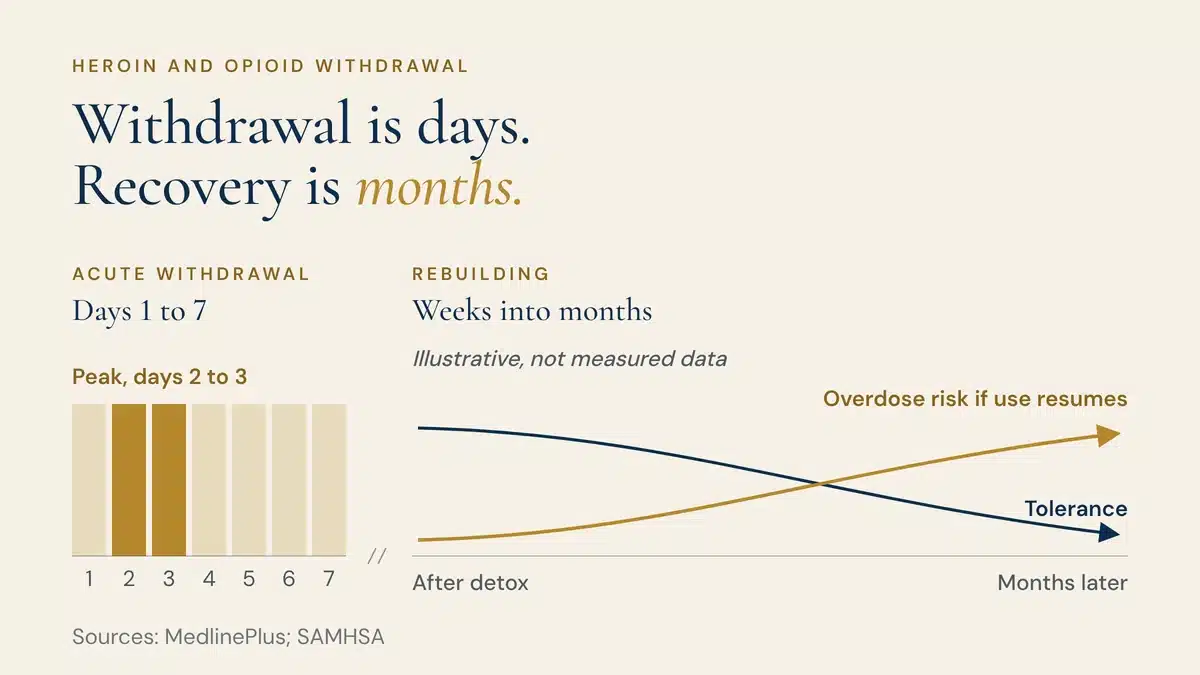
- According to NIDA, major heroin withdrawal symptoms peak between 24 and 48 hours after the last dose and subside after about a week; the course is miserable but rarely life-threatening on its own.
- Buprenorphine, methadone, and naltrexone are the three FDA-approved medications for opioid use disorder; MLJ offers buprenorphine and naltrexone and coordinates with a licensed program when methadone is the right choice.
- The weeks after detox carry the highest overdose risk, because tolerance falls faster than the habit does; every client leaving after opioid treatment is offered naloxone and shown how to use it.
- Lasting recovery depends on the months after detox: residential care of 30 to 90 days, medication continued where it helps, trauma and mental health treated alongside, and a planned step down.
How heroin addiction takes hold.
Heroin is an opioid made from morphine, which comes from the opium poppy. The National Institute on Drug Abuse explains that repeated use changes the physical structure and physiology of the brain, and that it can weaken decision-making, behavioral control, and the response to stress. Tolerance follows, so more of the drug is needed for the same effect, and with it physical dependence, in which the body has adjusted so thoroughly that stopping brings on withdrawal.
NIDA describes heroin use disorder as a chronic relapsing disease that goes beyond physical dependence, marked by drug-seeking that continues whatever the consequences. That is why willpower so rarely holds and why detox alone so rarely ends it: the brain that learned to need heroin is still the brain doing the deciding in the weeks afterward.
Signs families notice.
The signs families notice are usually behavioral before they are physical: money that does not add up, long bathroom visits, nodding off mid-conversation, sickness every morning that eases after a disappearance, a switch from smoking to injecting, using alone, a prior overdose, or a failed attempt to quit at home. Any one of these is reason to act now rather than wait for a clearer moment. Withdrawing at home is risky for a quieter reason: when it fails, the return to use comes at a lower tolerance.
Fentanyl in the heroin supply.
For most of its history the main danger in heroin was variable purity. That has been overtaken by contamination. The Centers for Disease Control and Prevention describes illegally made fentanyl as up to 50 times stronger than heroin, commonly mixed into heroin and other drugs, and impossible to detect by sight, taste, or smell. The Drug Enforcement Administration notes that dealers mix fentanyl into heroin, methamphetamine, and cocaine, and that two milligrams can be lethal depending on body size, tolerance, and past use. Test strips help, but the CDC warns they may miss more potent related compounds such as carfentanil.
Two consequences follow. Every purchase is a different drug, so a dose that was survivable last week may not be this week. And someone who believes they use heroin may in fact be dependent on fentanyl, which changes how withdrawal unfolds and when medication can safely start. Our pages on fentanyl addiction and the broader picture of opioid addiction cover that overlap, and the medical team assumes fentanyl exposure until history and testing say otherwise.
Withdrawal and medically supervised detox.
According to MedlinePlus, heroin withdrawal usually starts within 12 hours of the last use. Early symptoms are agitation, anxiety, muscle aches, tearing, runny nose, sweating, yawning, and insomnia; later come cramping, diarrhea, nausea, vomiting, dilated pupils, and goosebumps. The symptoms are very uncomfortable but not, in themselves, life-threatening. The medical risks are dehydration, electrolyte loss, and vomit inhaled into the lungs.
In practice, the first day brings restlessness and dread. NIDA places the peak between 24 and 48 hours after the last dose, when the body is at its worst and the pull to use is strongest. Over the rest of the first week the physical symptoms ease. Days eight through ten are quieter but not quiet: sleep is broken, energy low, mood flat, and cravings come in waves. If fentanyl is involved, onset may be delayed and the course longer; our detox timelines by substance compare the two side by side.
At the residence, medically supervised detox means withdrawal is scored on a standard scale, comfort medications are given as symptoms appear, fluids are replaced, and the timing of buprenorphine is set by your body rather than the calendar. Our page on opioid and fentanyl detox explains why that timing matters, and sleep in early recovery covers the symptom that lingers longest.
Medications for opioid use disorder, stated plainly.
Three medications are FDA-approved for opioid use disorder, and SAMHSA’s Treatment Improvement Protocol 63 treats each as legitimate treatment rather than a substitute addiction. Buprenorphine is a partial agonist: it relieves withdrawal and craving without producing a high, and its ceiling effect on breathing makes it far safer in overdose than heroin. It is started here once withdrawal is clearly underway and continued through residential care and beyond. Naltrexone blocks opioid receptors entirely and is available as a monthly injection; it can only begin after a fully opioid-free interval, about a week after heroin, so it is a decision made at the end of detox. Methadone is a full agonist with the longest evidence base, but it can only be dispensed for opioid use disorder through a federally licensed opioid treatment program. MLJ is not one, so when methadone is right, or you arrive already taking it, we coordinate with a program.
There is no single correct choice, and the medical team decides it with you, based on your history, your work, and your preferences. What TIP 63 and the wider evidence do not support is detox followed by no medication at all, a path associated with high rates of return to use and overdose. Our guide to detox medications describes each option without dosing.
Residential treatment for heroin addiction at MLJ.
Heroin addiction treatment here happens in one private six-bed residence in Encino, which clients reach from across Los Angeles. Residential treatment of 30 to 90 days gives the rebuild room. The first task is identifying triggers precisely: not “stress” but the Sunday evening, the drive past a certain exit, the call from a particular person. The second is structure, because idle hours were where use lived, so the day fills with therapy, exercise, meals at set times, and work on things that matter. The third is cutting supply lines: numbers deleted, routes changed, and the people you used with told plainly that you have stopped.
Underneath, the reasons heroin worked get treated. PTSD treatment addresses the trauma heroin was quieting, and co-occurring disorder treatment takes on depression, anxiety, or chronic pain in the same plan. Peer support, whether Narcotics Anonymous or another community, begins while you are still in the house.
After residential: PHP, IOP, relapse prevention and naloxone.
MedlinePlus is blunt: most opioid overdose deaths occur in people who have just detoxed. Withdrawal lowers tolerance, so a dose that was routine a month ago can now stop someone’s breathing, while the habit, the dealer’s number, and the memory of the old dose remain intact. With fentanyl in the supply, that gap is wider.
Naloxone, available as a needle-free nasal spray, rapidly reverses an opioid overdose; NIDA notes that potent opioids may require more than one dose and that 911 should still be called immediately. Every client who leaves MLJ after opioid treatment, and every family member who wants it, is offered naloxone and shown how to use it. The step down through partial hospitalization and IOP, and often transitional living, is planned rather than improvised, with relapse prevention built in and medication continued. Understanding why relapse happens is part of the work, and our page on the first 24 hours after a relapse exists so that a lapse is far less likely to be fatal.
How families can help.
Keep naloxone in the house and learn to use it. Plan the conversation in advance, with a specific ask and a specific place ready, and expect refusal the first time; our page on when a loved one refuses treatment covers what to do next. Once someone is in care, family therapy helps rebuild trust and teaches everyone what recovery asks of the household. Many first calls to our Encino drug rehab are made by someone else, and our resources for families explain how to help without carrying it alone. When you are ready, you can verify insurance benefits confidentially or start with the admissions team.