
Published by the Clinical Team at My Limitless Journeys. Reviewed under board-certified psychiatric oversight.
The pattern we see at intake
A man in his late thirties arrives for cocaine and alcohol treatment. In the third or fourth session he mentions, almost as an aside, that he has never been able to read a contract without walking around the room, that he was called disruptive from the age of seven, and that a friend’s Adderall before a pitch was the first time his head had ever been quiet.
That last sentence is the one to notice. Stimulants make most people feel accelerated. A person with untreated ADHD frequently reports the opposite: calm, focus, a sense of finally being able to sit still. It is a clinically meaningful observation, and it is one that never appears in a chart unless somebody asks.
How common this actually is
Adult ADHD is neither rare nor mostly childhood-onset in the diagnostic record. In a 2023 national survey reported by the CDC in Morbidity and Mortality Weekly Report, an estimated 6.0% of US adults had a current ADHD diagnosis — around one in sixteen, or 15.5 million people — and approximately 55.9% of them received that diagnosis at age eighteen or older.
The overlap with substance use is substantial. SAMHSA’s advisory on adults with ADHD and substance use disorders reports that in the National Comorbidity Survey Replication, 15.2% of adults with ADHD also met criteria for a substance use disorder, compared with 5.6% of adults without ADHD. Running the comparison the other way, roughly 10.8% of people seeking substance use treatment meet ADHD criteria, with some studies reporting figures as high as 23%. Whichever direction you look from, this is not an edge case; it is one of the most common co-occurring pictures in addiction medicine, alongside the ones we describe in co-occurring disorders.
Why they travel together: three mechanisms
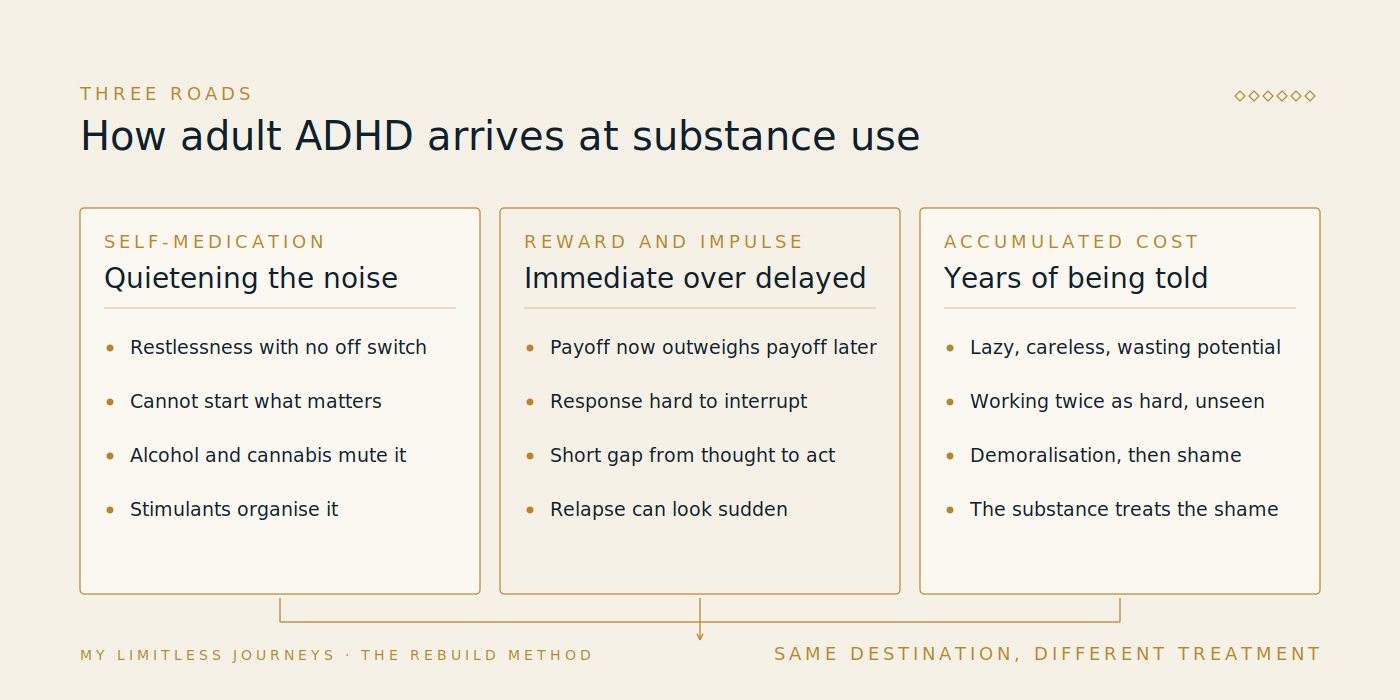
Self-medication. Untreated ADHD is not simply distractibility; it is an aversive internal state. Restlessness, mental noise, an inability to start things that matter, and — for many adults — emotional reactivity that arrives faster than thought. Alcohol quietens it. Cannabis quietens it. Stimulants organise it. SAMHSA’s advisory names this directly, noting that misuse of alcohol and marijuana by people with ADHD may be an attempt to relieve the tense feelings that accompany the disorder. Nobody sets out to develop a dependency; they set out to be able to finish a piece of work.
Reward and impulsivity. ADHD involves a reward system weighted toward immediate, salient payoff over delayed benefit, plus reduced capacity to interrupt a response once it has started. That combination describes the architecture of addiction with uncomfortable precision. It is also why the gap between “thinking about it” and “doing it” is shorter in this population, and why relapse can look so sudden from the outside.
Accumulated consequence. The third route is slower and more human. Twenty years of being told you are lazy, careless or wasting your potential — while working twice as hard as the people around you — produces a specific kind of demoralisation. The substance treats the demoralisation rather than the attention. And the emotional dysregulation that so often travels with adult ADHD, which we cover in emotional dysregulation in ADHD, makes the whole cycle harder to interrupt.
Why we cannot diagnose you this week
Active intoxication and withdrawal reproduce the entire ADHD symptom list. Stimulant withdrawal produces poor concentration, restlessness and irritability. Alcohol withdrawal produces agitation and cognitive fog. Chronic cannabis use produces a flattening of motivation that is hard to distinguish from inattentive presentation. Assess someone in week one and you will diagnose the withdrawal.
A defensible assessment therefore does three things. It waits for a period of stability, commonly around four weeks of abstinence, so that current symptoms can be read for what they are. It goes backwards, looking for evidence of impairment before substance use began — school reports, a parent’s account, a partner’s recollection — because ADHD is a developmental condition and childhood history is diagnostic rather than optional. And it uses structured instruments alongside the clinical interview, of the kind SAMHSA describes, rather than resting on a single questionnaire. This is precisely the kind of sequencing our levels of care for co-occurring disorders page is built around, and one of the practical arguments for residential treatment: four weeks of continuous observation by one clinical team is worth a great deal more than three outpatient appointments.

The stimulant conversation, honestly
Two fears sit on either side of this. Families fear that treating ADHD with a controlled stimulant is handing a drug problem a prescription. Clients fear that a history of addiction will disqualify them from a medication that might have changed their twenties.
The evidence is more reassuring than either fear suggests. Meta-analytic work on childhood stimulant treatment and later substance use has found no evidence that treatment increases the lifetime risk of substance use or dependence, and SAMHSA’s advisory states that the abuse risk associated with stimulant medications does not appear to be appreciably higher in people with co-occurring ADHD and substance use disorders than in those with ADHD alone. That is not the same as saying prescribing is simple here. It means the decision is clinical rather than automatic in either direction.
In practice, prescribing for someone with a stimulant use history is done with structure: a clear diagnosis, a single prescriber, extended-release formulations rather than short-acting ones, defined quantities, monitoring, and an explicit agreement about what happens if things drift. Non-stimulant options exist and are genuinely useful for some people, particularly where the substance history involves cocaine or methamphetamine. Access is also a live practical issue — the same CDC report found that 71.5% of adults taking stimulant medication had difficulty filling a prescription in the previous twelve months because the medication was unavailable, which is a real destabilising factor worth planning for rather than discovering.
What helps besides medication
Medication, where it is used, addresses the attentional core. It does not install habits, repair a decade of missed deadlines, or teach anyone to tolerate a difficult feeling without reaching for something. That work is behavioural and it is where most of the durable gain comes from.
Cognitive behavioural therapy adapted for adult ADHD targets the specific mechanics: how tasks get initiated, how time gets estimated, how avoidance builds. Our approach to CBT in this context is about externalising executive function rather than exhorting people to try harder — one calendar, one list, visible timers, an environment doing the work that internal regulation cannot yet do reliably. Dialectical behaviour therapy skills, particularly distress tolerance and emotion regulation, address the reactivity that so often precedes use. Sleep and exercise are not lifestyle advice here; both measurably affect attention, and both are treated as clinical work in the Body domain of the Rebuild Method.
And then there is the part clients rarely expect to matter most: the reframe. Being told, at thirty-eight, that the last twenty years had a name and a mechanism is frequently the moment the shame loosens. Shame is fuel for use. Removing it is treatment, not comfort.
Sequencing, in plain terms
First, safety: managed withdrawal where it is needed, which for stimulants means the crash, the sleep debt and the depressive dip described in stimulant withdrawal. Second, stability: sleep, food, routine, and enough time abstinent for a clean look at the baseline. Third, assessment: structured, developmental, collateral-informed. Fourth, a shared decision about treatment, made with the substance history on the table rather than hidden from the prescriber. Fifth, integration — both conditions managed by one team, indefinitely, because SAMHSA is candid that formal guidelines for this combination remain limited and the work is therefore individualised.
What does not work is treating one and deferring the other. Treat the addiction alone and the untreated ADHD steadily erodes the structure recovery depends on. Treat the ADHD alone while use continues and you are titrating a medication against a moving target. Our page on ADHD treatment sets out how we hold both at once.
Frequently asked questions
I was only ever diagnosed as an adult. Is that real ADHD?
Yes, provided the developmental history supports it. More than half of adults with a current diagnosis received it at eighteen or older. What a good assessment looks for is evidence of impairment early in life, even where nobody named it at the time — which is common for girls, for high-IQ children who compensated, and for anyone whose household had louder problems.
Will a history of cocaine use stop me from being prescribed a stimulant?
Not automatically, and it should not be decided by a rule. It is weighed alongside the strength of the diagnosis, the substance history, your current stability and what monitoring is available. Non-stimulant options are considered seriously in this situation, and for some people are the better answer.
I have been taking a friend’s prescription to get through work. Is that a substance problem?
It is at minimum a warning sign, and it is worth saying out loud to a clinician. It often signals untreated ADHD, and it carries real risks: an unknown dose, no monitoring, escalation, and the legal exposure of a controlled substance not prescribed to you.
How long do I need to be abstinent before an assessment?
Around four weeks is a common working threshold, longer where use was heavy or prolonged. It is a clinical judgment rather than a fixed rule, and preparatory work — history, collateral information, screening instruments — can begin well before the formal evaluation.
Does treating ADHD reduce the chance of relapse?
We cannot promise an outcome, and the research on treating both conditions together is still developing. What we can say clinically is that untreated ADHD makes every component of a recovery plan harder to sustain — appointments, routine, sleep, emotional regulation — and that removing that friction tends to make the rest of the work possible.
If the substance was doing a job your brain could not do unaided, that is worth assessing properly rather than guessing at. We treat both conditions with one team, under psychiatric oversight.
Keep reading: ADHD treatment · Emotional dysregulation in ADHD · Co-occurring disorder treatment · Cocaine and stimulant addiction treatment · CBT in addiction treatment